


What sets Ipamorelin apart from its predecessors
Ipamorelin, catalogued in the development database as NNC 26-0161, is a pentapeptide with the sequence Aib-His-D-2-Nal-D-Phe-Lys-NH2. Five amino acids, two of them D-configured and one non-natural — the specific structure is responsible for both receptor specificity and stability against peptidases.
The compound was developed in the late 1990s by Novo Nordisk in Denmark. The key finding from Raun et al. (European Journal of Endocrinology, 1998) still shapes practice: Ipamorelin releases GH with a selectivity resembling endogenous GHRH — without the ACTH, cortisol and prolactin rises seen with other GHRPs. Even at doses more than 200-fold above the effective GH-releasing dose, ACTH and cortisol levels stayed quiet.
That selectivity is at the core of its popularity. Anyone trying to avoid the catabolic cortisol side effect from GHRP-6 (or the prolactin reaction) practically lands on Ipamorelin by default.
Mechanism in detail
Ipamorelin binds selectively to the Growth Hormone Secretagogue Receptor type 1a (GHS-R1a) — the same receptor activated by the endogenous hunger and GH signal molecule ghrelin. Activating this receptor triggers an intracellular cascade in the pituitary somatotrophs:
- Mobilisation of intracellular calcium
- Activation of protein kinase C (PKC)
- Activation of mitogen-activated protein kinase (MAPK)
- Exocytosis of stored GH vesicles
- Stimulation of GH gene transcription
Result: a pulse-like GH rise inside minutes of the injection, followed by a fall back to baseline across 60–90 minutes. This pulsatile release resembles the natural GH secretion pattern — one reason some users find Ipamorelin “more physiological” than exogenous HGH with its constantly elevated baseline.
The GH pulse leads secondarily to a rise in IGF-1 in the liver. IGF-1 mediates a substantial part of the anabolic and regenerative effects of growth hormone: muscle protein synthesis, collagen formation, lipolysis in fat tissue, boosted cell proliferation.
What Genopharm ships
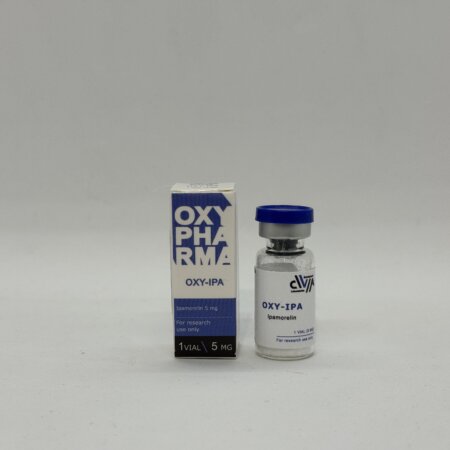
Genopharm delivers the 5 mg vial as lyophilised peptide without additives. At typical community doses (200–300 µg per injection, 1–2× daily), one vial lasts about 8–12 days. A standard 8-to-12-week cycle then needs 6–10 vials.
Where users reach for Ipamorelin
Reports converge on several profiles:
- Recovery between training sessions — faster bounce-back, less lingering DOMS
- Fat-loss support, particularly visceral
- Holding or building lean muscle in combination with training and protein
- Better sleep quality, particularly with an evening injection
- Positive effects on joints, tendons, connective tissue
The effects are subtler than under anabolic steroids and need time. First changes on sleep and energy usually after 1–2 weeks. Visible shifts in body composition typically after 6–12 weeks — training and nutrition permitting.
Why the evening injection
The body produces natural GH in pulses, with the biggest peaks in the first deep-sleep phases. An Ipamorelin shot just before bed amplifies that natural peak — hence the community recommendation to inject at night.
Anyone also injecting in the morning or post-workout should leave at least 3–4 hours between doses to avoid receptor desensitisation.
Important: Ipamorelin works best on an empty stomach. Insulin and blood sugar suppress GH release. Someone injecting 30 minutes after a carb snack produces a much flatter peak than under a fasted injection. For the evening dose that means 2–3 hours after the last meal.
The classic stack with CJC-1295 DAC
In the peptide community the combination with CJC-1295 DAC is basically default. The two peptides activate different receptors: Ipamorelin the ghrelin receptor, CJC-1295 the GHRH receptor. The combined GH release is notably stronger than the sum of the single effects. CJC-1295 DAC lifts the weekly baseline; Ipamorelin adds pulsatile peaks at each injection.
Controlled clinical trials on this combination don’t exist; the practice rests on pharmacological plausibility and empirical experience.
Safety and legal status
Compared to other peptides in this category, Ipamorelin has a favourable safety profile. Reported side effects are mostly mild and short-lived: injection-site irritation, mild water retention (hands, face), transient joint aches at higher doses, occasionally fatigue immediately after the shot.
The theoretical core concern is chronically elevated IGF-1 levels. IGF-1 promotes cell division — in active malignancy or an oncological history, use is advised against.
Legal picture: not approved as a medicine in the US, EU or UK. Distribution as a research chemical, grey zone. WADA Prohibited List 2026, category S2, banned at all times for tested athletes.
Instructions
Reconstitution
The 5 mg vial is reconstituted with bacteriostatic water. Recommended dilutions:
- 2 ml water → 2.5 mg/ml → 0.1 ml = 250 µg
- 2.5 ml water → 2 mg/ml → 0.125 ml = 250 µg
- 5 ml water → 1 mg/ml → 0.25 ml = 250 µg
For the 5 ml dilution, insulin syringes with a 100-unit scale are handy — a 250 µg dose lands exactly at 25 insulin units.
Spray water slowly at the inner wall, then roll for 30 seconds. Do not shake.
Dosing
| Parameter | Study literature | Community practice |
|---|---|---|
| Single dose | 200–300 µg | 200–300 µg |
| Frequency | 1–3× daily | 1–2× daily, usually evening |
| Cycle length | 8–12 weeks | 8–12 weeks, then 4-week break |
| Route | Subcutaneous | SC, abdomen or thigh |
Injection timing matters more than the absolute dose. An evening shot 30–60 minutes before sleep syncs the GH peak with natural deep-sleep phases. If you’re running two injections per day, add a morning fasted dose or one right after training.
Because of the low price per vial and the tiny injection volume, Ipamorelin is one of the most accessible GH secretagogues for peptide newcomers.
Injection technique
Insulin syringe 30G × 8 mm, subcutaneous into the abdominal wall or the outer thigh. Lift a skin fold, insert at 45° or 90°, inject slowly. Rotate sites to avoid local reactions.
Wait 30 seconds after injection before pulling the needle out — prevents solution backflow.
Storage
Before reconstitution: fridge at 2–8 °C, kept from light.
After reconstitution: fridge at 2–8 °C, use within 2–4 weeks. Do not freeze — peptide folding is destroyed by freeze-thaw. With twice-daily use at 250 µg, a 5 mg vial covers about 10 days — well inside the activity window.
Combining with CJC-1295 DAC
Separate injections are preferable for sterility. Practical setup: CJC-1295 DAC once a week in one shot (1–2 mg), Ipamorelin 1–2× daily (200–300 µg) in a separate syringe. Some users mix both peptides in one syringe — not optimal from a sterility angle, workable if both vials come from clean batches.




Reviews
There are no reviews yet